Chanel Robinson achieved exactly what the gold rush of blockbuster weight-loss drugs promised: She lost nearly 100 pounds, lowered her cholesterol to normal levels and reined in her polycystic ovary syndrome.
Yet, nearly three years into her journey on Mounjaro, the 30-year-old from Atlanta, Ga., is discovering the hidden costs of the slimmed-down life.
Robinson experiences muscle fatigue daily, feeling physically weak, frail and often cold. Robinson said she experiences bursts of sluggishness sporadically during the day, and has trouble with basic tasks like opening a jar. “It shouldn’t be this difficult,” she said.
GLP-1 drugs like Ozempic, Mounjaro and Zepbound have been a success for public health and the pharmaceutical companies that make them. Obesity rates are falling, the volume of food consumed in America is declining and retailers report a slump in sales of plus-size apparel. It has improved health and happiness for millions of people.
But for at least some of the 13 million Americans taking them, losing muscle along with fat is an unexpected downside that isn’t broadly discussed or immediately apparent.
The drugs can cause rapid and significant loss of lean muscle mass, up to 10%, comparable to a decade or more of aging, according to an analysis published by the American Diabetes Association.
The loss of lean tissue is similar to weight loss from dieting, but the magnitude over a short period can lead to frailty, instability and lack of coordination, doctors and researchers say. Another concern is that losing muscle could slow down patients’ metabolism, leading to weight regain.
“We are curing obesity by encouraging frailty,” said Daniel Green, principal research fellow at the University of Western Australia, who contributed to the analysis. Many taking weight-loss medications initially lose fat and feel great, but quickly start to feel weak and lethargic, he said.
Green’s research showed that the rate of muscle loss could be slowed significantly by regular strength workouts. “It should say ‘must be taken with resistance training’ on the box,” he said.
Drugmakers say weight-loss drugs should be taken only on the advice of a physician and as part of a long-term plan that includes diet and exercise.
A spokesperson for Eli Lilly, maker of Zepbound, said Food and Drug Administration guidelines say it should be used “with increased physical activity.” The spokesperson added: “Sustainable weight loss is about more than a number on a scale.”
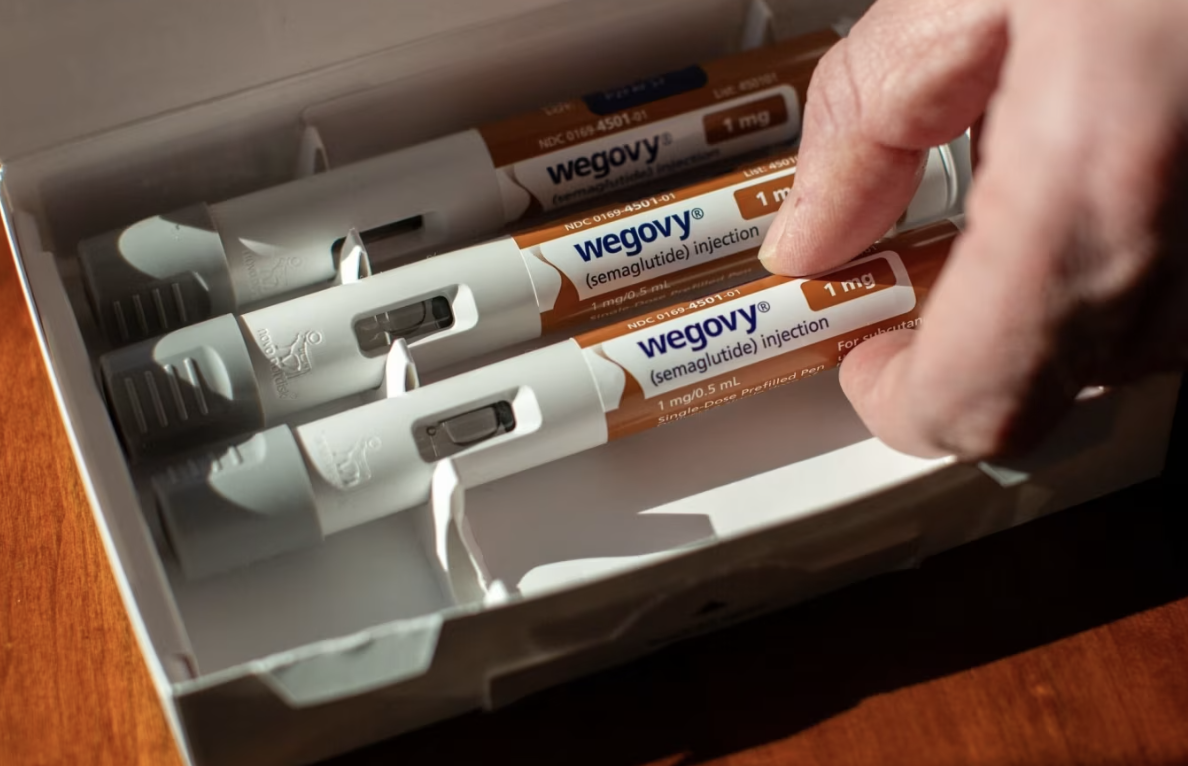
Both Eli Lilly and Novo Nordisk said clinical trials showed users did lose some lean muscle tissue, though at far lower rates than fat. Liz Skrbkova, a spokeswoman for Novo Nordisk, said that trials for its drug Wegovy showed changes in muscle mass didn’t “significantly differ” from patients who took a placebo. Eli Lilly said users lost three times more fat weight than lean tissue.
Rayna Kingston, 30, from Denver, said her injections of Zepbound left her feeling so tired the following day that she struggled to complete anything other than basic tasks. She said she shifted her dose to a Sunday because Mondays were her least busy day. Her partner would bring her meals in bed because she felt so weak.
She stopped exercising, and said her doctor didn’t give her any guidance on strength training or muscle maintenance. “I was relying on Reddit forums to understand what was happening to my body,” she said. She got so frustrated with the fatigue she came off the medication just under two months later.
Experts say that losing muscle at such a rate can be especially dangerous for those over 50 or with osteoporosis or limited mobility as it could lead to an increased risk of injury. “Loss of muscle mass is detrimental to moving around and quality of life, but it is also not safe,” said Katsu Funai, associate professor at the University of Utah.
Elderly Americans are set to be able to get GLP-1s from Medicare from July.
There is also pushback from doctors and regulators against using weight-loss drugs as a “quick fix” to lose a bit of weight.
People who take GLP-1s regain weight four times faster than those who lose weight through lifestyle interventions, and weight regained is often mostly fat, according to a recent analysis published in the British Medical Journal. There currently are few, if any, guidelines or studies on de-prescribing the drugs, researchers say.
The nurse practitioner who prescribed Robinson the medication didn’t warn her that resistance training is essential to maintaining muscle mass, Robinson said. She said she regrets not exercising and now does Pilates once a week.
In the haste to disrupt the obesity epidemic, weight loss has been treated as the singular, undisputed metric of success, which experts say is problematic.
“People worship body weight as an outcome measure because it’s simple, quick and inexpensive,” said Green. “But what matters is fat and muscle mass, which is more expensive to measure as it requires an MRI.”
Grace Parkin, 34, a property manager from Sheffield, England, has lost 125 pounds after she started taking Mounjaro in 2024. “I don’t care about my muscle mass as long as I’m a healthy weight,” she said.
The doctor who prescribed the drug didn’t tell her to exercise, though the pharmacy that sold the medication gave her information on exercise and protein intake, she said.
She didn’t exercise and said she soon felt side effects: a “deathly cold, from the inside” likely because of the drug. Still, she vowed to keep going, saying the weight loss was worth it.
In response to some of the side effects, drug companies are hoping to develop weight-loss treatments aimed at preserving or even building lean muscle mass.
German drugmaker Boehringer Ingelheim recently said it had promising results from one such drug. Eli Lilly last September halted a trial of a similar drug.
While weight-loss medications are designed as lifelong treatments for chronic diseases, namely obesity and Type 2 diabetes, they are increasingly marketed as lifestyle fixes.
Tennis superstar Serena Williams, who used GLP-1s to slim down after having children, was featured in this year’s Super Bowl commercial promoting telehealth company Ro’s weight-loss medication.
Women may be particularly vulnerable to the drugs’s side effects, which can also include nausea, diarrhea, migraines and rarer cases of pancreatitis.
A study last year from a university hospital in Turin, Italy, showed that women are more prone to adverse reactions to weight-loss drugs than men, including muscle loss.
Green, the researcher, said the issue is of particular concern to those taking GLP-1s recreationally and who don’t have much muscle mass to begin with. Others say a lack of oversight is compounding the issue.
“Patients are self-reporting, and telehealth companies don’t have the patient in front of them to conduct a proper medical assessment,” said Rupal Mathur, an internist in Houston whose practice specializes in weight loss.
She said medical spas are prescribing off-label drugs that don’t meet the criteria set out by the FDA that justify a prescription.
The number of people taking weight-loss drugs who are not living with obesity or Type 2 diabetes is difficult to track since it is unregulated.
However, an analysis by the FDA from 2023 found that more than half of new Ozempic and Mounjaro users didn’t have Type 2 diabetes.
Scientists are calling for more clinical trials to pin down the full effects of weight-loss drugs on muscle loss in different demographics.
“The only studies that have been done have looked at people living with obesity or Type 2 diabetes,” said Green. “That makes it all the more concerning for those using weight-loss drugs in an ad hoc or unregistered way.”


 5 min
 Copyright 2020, Dow Jones & Company, Inc. All Rights Reserved Worldwide.







